Move liability decisions earlier
Examine exposure, channel and cell-family scenarios while there is still room to change the experimental or development plan.


CARDIX | CARDIAC SAFETY & ELECTROPHYSIOLOGY
Bring cardiac-liability questions forward, focus confirmation work and plan for likely co-medications. CardiX connects multichannel evidence, tailored virtual cell families and uncertainty analysis to the next development decision.
Tailored in silico cardiac safety modeling for safety pharmacology teams: connect hERG, calcium and sodium channel evidence to cellular electrophysiology, biological variability and drug-combination questions.
THE BUSINESS CASE
For preclinical safety and R&D program leaders, the value is a clearer decision before additional time and investment depend on an uncertain result. CardiX helps distinguish findings that remain consistent across plausible scenarios from those that need more data or a different development plan.
Examine exposure, channel and cell-family scenarios while there is still room to change the experimental or development plan.
Prioritize confirmation work around sensitive boundaries and candidate mitigation scenarios that need experimental assessment.
Bring likely co-medications into the assessment and plan the nonclinical evidence needed for later scientific and regulatory discussions.
THE SCIENTIFIC QUESTION
A single potency value or a single simulated condition gives a limited view of cardiac electrophysiology. The development question is how the combined response behaves across relevant channels, concentrations, cell characteristics and the uncertainty in the evidence.
CardiX brings these dimensions into a tailored analytical system. Teams can investigate which conclusions hold across the scenarios that matter, where the response changes, and what experiment would most usefully reduce uncertainty.
MULTICHANNEL EFFECTS
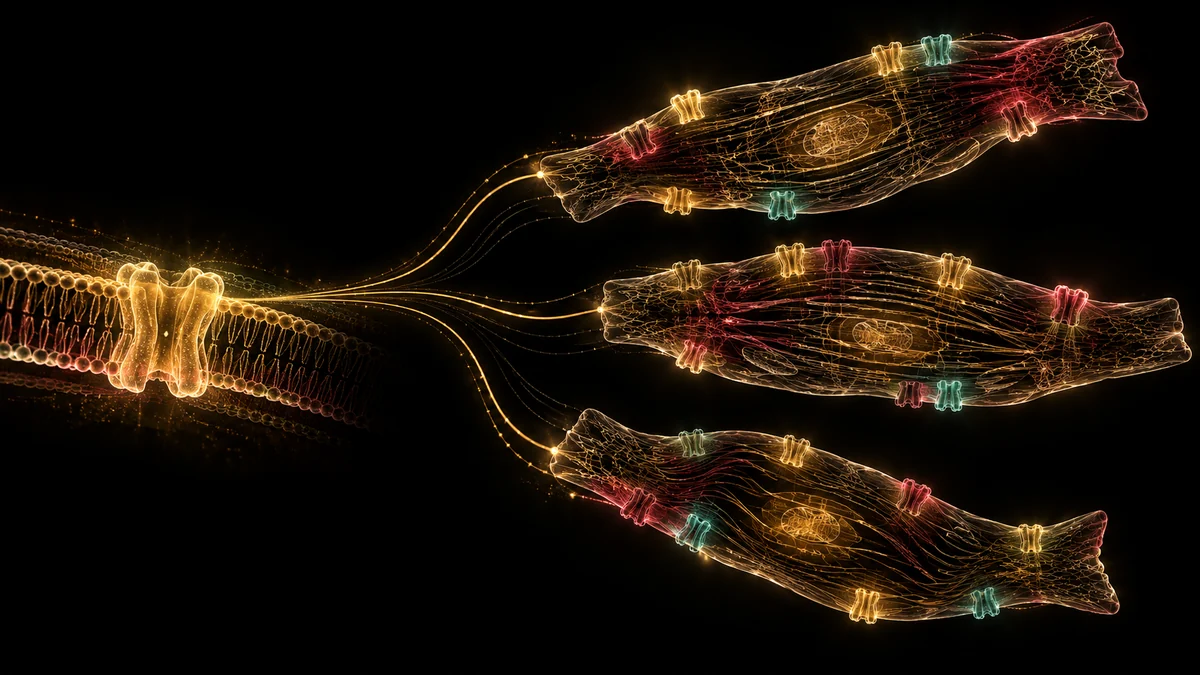
Cardiac safety assessment has historically placed strong emphasis on hERG potassium-channel inhibition and its IC50: the concentration associated with half-maximal inhibition under the assay conditions. Multichannel pharmacology considers this evidence alongside a compound’s effects on calcium, sodium and other potassium channels. These contributions interact: one effect may reinforce or counter another, and their balance changes with exposure.
The combined response can be nonlinear. A modest change in one input may have little effect in one cellular context and a much larger effect in another. CardiX examines the resulting electrophysiology rather than treating each channel finding as an independent answer to the development question.
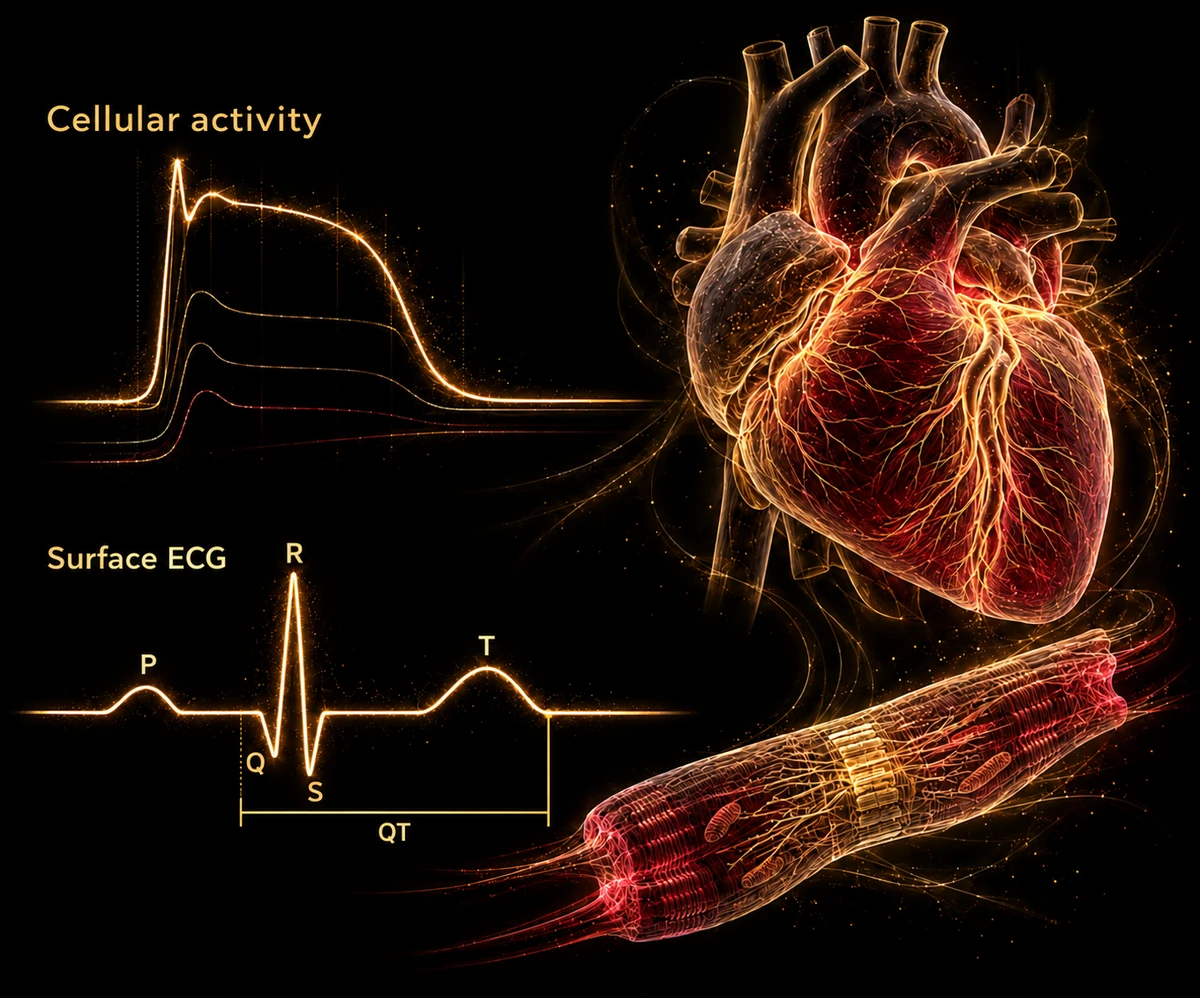
We follow how these combined effects alter the cardiac action potential, including action-potential duration (APD) and the pattern of repolarization. These cellular responses help frame QT-related follow-up questions. The QT interval comes from the surface ECG and reflects ventricular depolarization and repolarization; connecting a cellular finding to clinical QT or arrhythmia risk requires additional evidence. This distinction helps teams choose the next measurement and interpret what a modeling result actually supports.
Channel coverage and the quality of the available concentration-response evidence shape the study. Measured profiles, potency estimates and their uncertainty are considered together, so the analysis can show which channel contributions deserve closer investigation and which conclusions depend on incomplete inputs.

LABORATORY CONTEXT & VIRTUAL CELL FAMILIES
Virtual cell families are populations of cardiac cell models that represent plausible differences in electrophysiology. They can differ in baseline behavior, response to pacing and the balance of channel activity, while assay conditions also affect what is observed. Comparing this ensemble of cardiac cell models helps teams assess how early cardiac-liability findings depend on plausible cellular variability.
ADETERA uses available cell measurements, assay context and development objectives to define the target characteristics. Where the evidence supports calibration, the fit is assessed against agreed comparison criteria. Members of a virtual family can represent plausible variation around that reference, helping teams examine whether a compound’s response remains consistent as cellular characteristics change.
The study keeps the characterization evidence, calibration assumptions and remaining differences visible. Missing measurements or a limited reference dataset constrain what can be inferred; no virtual family is assumed to reproduce every aspect of the laboratory cells. These limits help define the next measurements and the conditions under which a comparison is useful. The resulting capability is tailored to the team’s experimental context, with conclusions reviewed alongside the evidence that supports the match.

ROBUSTNESS, ATTRACTORS & STABILITY LANDSCAPES
IC50 estimates and other channel parameters vary between measurements, assay conditions and repeats. Replicate measurements and reported uncertainty help define plausible input ranges for the study. A result at one selected value may lie close to a boundary where nearby plausible values change the response. Reviewing only the nominal condition can miss that sensitivity.
CardiX combines classical electrophysiology metrics with attractor, trajectory and correlation analyses. These complementary views help teams compare waveform behavior, relationships between responses and departures that may be less apparent in an isolated endpoint.
Parameter sensitivity analysis examines how the modeled response changes when uncertain inputs are varied, providing model-informed support for nonclinical development decisions. Stability landscapes help identify windows in which modeled behavior remains consistent and regions where it shifts, so the team can prioritize uncertain boundary cases and the next measurements. A stable modeled window does not by itself establish a clinically safe exposure range.

CO-MEDICATIONS & DRUG-COMBINATION LIABILITY
Drug–drug interaction (DDI) questions arise when a development compound will be used alongside other medicines. Their cardiac ion-channel effects can overlap, reinforce or offset one another. Examining each compound separately can leave combination-specific questions unresolved: the relevant comparison is how the combined exposure changes cellular behavior and which combinations deserve focused confirmation.
CardiX investigates combined pharmacodynamic effects across the available channel profiles and specified concentrations. When pharmacokinetic interactions are expected to change exposure, relevant exposure scenarios can be supplied for the electrophysiology assessment; the channel analysis is not a substitute for a pharmacokinetic interaction study.
These comparisons help teams prioritize co-medication scenarios, plan confirmation studies and investigate candidate mitigation approaches. They can also organize the questions and supporting evidence for regulatory scientific discussions, while keeping study-specific assumptions and remaining validation needs explicit.
FROM EVIDENCE TO A DEVELOPMENT DECISION
The available data, the laboratory context and the consequences of the decision determine the scope. CardiX can support an initial scientific question and evolve into a repeatable system for the team’s continuing work.
A SYSTEM BUILT FOR YOUR TEAM
ADETERA develops and configures CardiX systems around the client’s scientific question and operating environment. Delivery can include a standalone analytical system, an optimized method, an automated workflow or integration into an existing environment, with the scope agreed around how the team will use the results.
Where appropriate, the work can draw on established electrophysiology foundations such as O’Hara–Rudy, alongside ADETERA methods selected for the client’s question. The study defines the relevant cell behavior, comparisons and evidence needed to interpret the outputs.
Proprietary scientific methods. ADETERA commercializes proprietary mathematical models and analytical methods through CardiX. Public materials describe the questions, capabilities and intended outputs; proprietary model structures and implementation details are not published.
QUESTIONS ABOUT CARDIX
Useful inputs include ion-channel concentration-response measurements, hERG and other channel IC50 estimates, units, assay conditions and evidence of variability. Reference cellular recordings help define the virtual population; relevant compound concentrations and co-medications define the exposure scenarios. ADETERA reviews the coverage and limitations before agreeing on the questions a study can address.
Available hERG evidence can frame an initial question. The scope must reflect the missing channel and cell-context evidence; a hERG-only input set cannot answer every multichannel or combination question. A first study can help identify which additional measurements would be most useful.
Yes. Virtual cell families can be configured around the client’s reference cell behavior, assay conditions and study objectives. The available experimental evidence determines how that fit is assessed and which assumptions remain open.
IC50 describes the concentration associated with half-maximal inhibition under the assay conditions; it is not itself a clinical safety threshold. Potency estimates for hERG and other channels carry variability. Comparing plausible ranges helps show whether a finding is consistent or depends on a narrow choice of parameters, and whether a nearby boundary deserves targeted confirmation.
No. Action-potential duration describes the electrical response of a cell; QT is measured on the surface ECG and reflects ventricular depolarization and repolarization across the heart. Cellular simulations can investigate responses relevant to QT-prolongation questions, but they do not directly establish a patient’s QT interval or arrhythmia risk. Interpretation requires the appropriate experimental and clinical evidence.
CardiX examines the combined cardiac electrophysiology effects of specified compounds and exposure scenarios. Pharmacokinetic changes to exposure require suitable input evidence or separate assessment. The resulting comparisons help prioritize combination questions and experimental follow-up.
The analysis can help organize nonclinical questions, supporting evidence and follow-up plans for scientific and regulatory discussions. Its use depends on the study’s context, evidence and validation; the output alone is neither a clinically validated prediction of arrhythmia nor a guarantee of regulatory acceptance.
Engagements are tailored to the client: a focused analysis may lead to a standalone system, an optimized analytical method, or an automated and integrated workflow. ADETERA’s proprietary methods are commercialized within that agreed scope.
FROM MEASUREMENT TO MODELING QUESTIONS
In an anonymized PlateX project, noisy cardiomyocyte proxy recordings were processed and reconstructed for cellular action-potential assessment. Concentration-related waveform features and separately measured hERG-current data helped frame directions for later CardiX work. That subsequent simulation stage is outside the case itself.
Read the cardiac signal reconstruction caseSTART A SCIENTIFIC CONVERSATION
Tell us which development decision is approaching, what channel and cell data are available, and which exposure or co-medication questions remain unresolved.